When I worked in a busy family clinic, one of the hardest conversations was not diagnosing a ureteral stone. It was helping someone decide when to stop “toughing it out.” If you already know you have a ureteral stone and you are in a monitored trial of passage, you deserve a clear line in the sand: waiting is only safe when your pain is controllable, there is no infection, your kidney is not being harmed, and the overall risk still favors giving the stone time.
This guide walks you through the most common reasons a trial of passage should end, and what stone-removal options typically look like if you need help getting it out.
The goal of a trial of passage
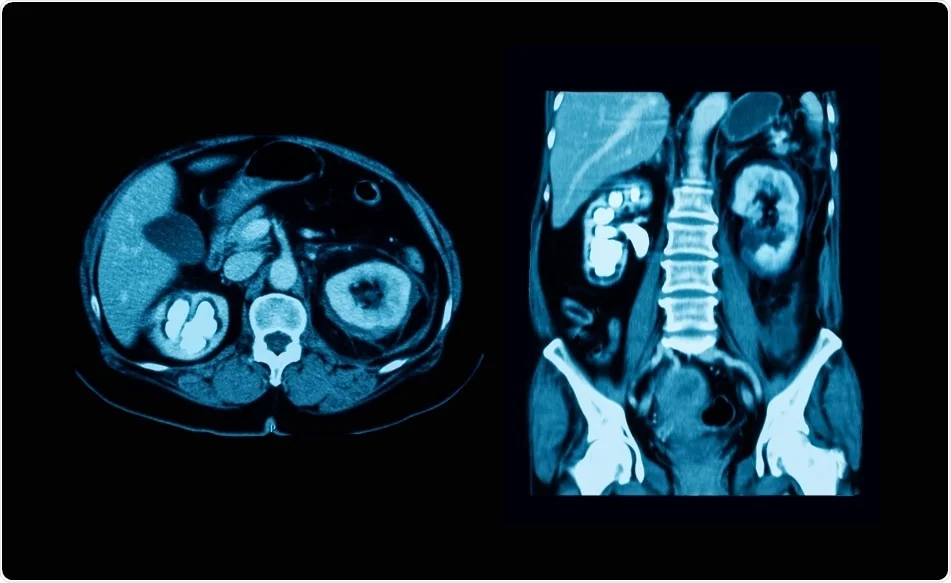
A trial of passage means you and your clinician have agreed to monitor symptoms and progress while the stone attempts to travel from the ureter into the bladder and out through urination. For many people, this approach is reasonable for smaller stones and stable symptoms, especially when the stone is closer to the bladder.
But waiting is not a test of willpower. A stone that is stuck can obstruct urine flow. Obstruction plus time raises the risk of kidney injury. How quickly that risk rises depends on how complete the blockage is, whether you have one or two functioning kidneys, and your overall health. Obstruction plus infection can become an emergency quickly.
How likely is it to pass?
In general, smaller stones are more likely to pass on their own, and stones in the lower ureter (closer to the bladder) tend to pass more often than stones higher up. Your clinician can usually estimate your personal odds based on stone size, location, and whether there is hydronephrosis or other signs of significant obstruction.
Even if the odds are good, the red flags below override the “wait and see” plan.
Stop waiting if pain is uncontrolled
Renal colic can be intense. Some pain is expected. The red flag is pain that is not controllable with the plan you were given.
What “uncontrolled” pain looks like
- You cannot keep pain at a tolerable level with prescribed medications.
- Pain is escalating instead of coming in waves.
- You cannot sleep, function, or hydrate because of pain.
- Ongoing vomiting or inability to keep fluids down, especially if paired with pain.
Why it matters: Uncontrolled pain is not only miserable. It can mean the ureter is in severe spasm, the stone is tightly wedged, or swelling around the stone is worsening. It can also lead to dehydration, which makes everything harder.
If your pain is not responding to the plan, call your urology team. If the pain is severe, or you cannot keep fluids down, go to urgent care or the emergency department depending on severity and what is available in your area. Needing stronger pain control is a valid medical reason to change course.
A quick medication note: Many clinicians use NSAIDs (such as ibuprofen or ketorolac) as first-line pain control for renal colic when they are safe for you. They are not appropriate for everyone, including some people with kidney disease, ulcers, or bleeding risk. Follow the plan you were given, and check before adding over-the-counter meds.
Stop waiting if the stone is not moving
Many people assume that if they still feel pain, the stone must be traveling. In reality, symptoms can fluctuate even when the stone is sitting in the same spot.
Clues the stone may be stuck
- Your symptoms have plateaued with no meaningful change for several days and you are not trending in the right direction. (This is not a strict rule, and it is not specific.)
- Imaging shows the stone in the same location on repeat scans.
- Your clinician notes persistent or worsening hydronephrosis, meaning urine is backing up toward the kidney.
Why it matters: A stationary stone can keep the ureter blocked. Even a partial blockage that drags on can stress the kidney. Follow-up is how we confirm waiting is still safe.
Also, a practical point: repeat CT scans are not always necessary. Depending on your situation, your clinician may use ultrasound, X-ray (for radiopaque stones), or low-dose CT to reduce radiation exposure while still checking for obstruction and progress.
Stop waiting if it has gone on too long
There is no single “right” number of days for every person, because the safest timeline depends on stone size, location, degree of obstruction, infection risk, pregnancy status, and how well you are tolerating symptoms.
That said, in everyday practice, a monitored trial of passage is usually measured in days to a few weeks, not months. If you are approaching the outer limit your clinician set, or you were never given a clear endpoint, it is time to recheck in.
Reasons time matters
- Ongoing obstruction can injure the kidney. Risk depends on how complete the obstruction is and how long it persists.
- Inflammation builds around the stone. Swelling can make spontaneous passage less likely as time goes on.
- Repeated emergency visits are a sign the plan is not working. If you keep needing rescue care, you deserve a more definitive solution.
If you are still in the thick of symptoms after the expected window, ask directly: “At what point do we stop observing and schedule removal?”
Stop waiting if kidney function is worsening
One kidney can compensate for the other, so you may not “feel” declining kidney function early. This is why clinicians watch objective signals: lab tests and imaging.
What your care team may monitor
- Blood tests that reflect kidney filtration, such as creatinine and estimated GFR.
- Ultrasound or CT findings showing hydronephrosis or worsening obstruction.
- Urine output trends, especially if output drops noticeably.
Why it matters: If kidney function is falling, the priority is to relieve obstruction, not to wait longer. Sometimes that means urgent decompression with a stent or nephrostomy tube, followed by stone removal once things are safer.
If you have a single functioning kidney, a kidney transplant, known chronic kidney disease, or you are older or medically frail, the threshold to intervene is often lower. Make sure your urology team knows your full history.
Fever with a ureteral stone is an emergency
This is the one I want you to remember without hesitation: fever or chills with a known obstructing stone can signal an infected, blocked urinary system. That combination can progress to sepsis.
One important nuance: some people with serious infection can be afebrile, especially older adults and people who are immunocompromised. If you feel suddenly very ill, do not wait for a thermometer to “prove it.”
Go to the emergency department now if you have
- Fever (for many adults, 100.4°F or 38°C or higher) or shaking chills
- Stone symptoms plus feeling faint, confused, extremely weak, or short of breath
- Rapid heart rate, new severe malaise, or symptoms that feel like you are “crashing”
- Stone symptoms plus burning urination and worsening flank pain, especially with fever
Do not try to manage this at home. Treatment may require IV antibiotics and urgent drainage of the kidney. Definitive stone removal is usually delayed until infection is controlled and you are stable.

Quick action checklist
If you are deciding what to do today, use this checklist:
- Emergency department now: fever or chills, uncontrolled vomiting, confusion, fainting, severe weakness, shortness of breath, or any signs of sepsis (including feeling severely unwell even without fever).
- Same-day urgent evaluation: pain not controlled with your plan, cannot keep fluids down, significantly reduced urination, or you feel worse instead of better.
- Call urology to reassess the plan: symptoms dragging on past the agreed timeline, repeat imaging shows no movement, or labs suggest kidney stress.
If you need a procedure
If observation is no longer the safest choice, your urologist will recommend an approach based on stone size, location in the ureter, your anatomy, pregnancy status, infection risk, and how urgently the blockage needs relief.
Ureteroscopy with laser lithotripsy
This is one of the most common options for ureteral stones. A small scope is passed through the urethra and bladder into the ureter. The stone is removed with a basket or broken into pieces with a laser.
- Best for: many mid and distal ureter stones, and stones that are not passing.
- What recovery is like: often outpatient, but you may have burning urination and bladder spasms for a few days.
- Common add-on: a temporary ureteral stent, which can cause urinary urgency, flank discomfort, and blood in urine until it is removed.
Shock wave lithotripsy (SWL or ESWL)
Sound waves are used from outside the body to break the stone into smaller fragments that you then pass in urine.
- Best for: select smaller stones based on size, composition, and location, typically when there is no infection and anatomy is favorable. In many settings it is more successful for stones in the kidney or upper ureter than for stones very low in the ureter.
- What recovery is like: less invasive, but you may pass fragments over days, and colicky pain can recur as pieces move.
- When it is often avoided: pregnancy, untreated infection, and some bleeding risks such as certain anticoagulants (your team will advise you).
Temporary drainage: ureteral stent or nephrostomy tube
If there is infection with obstruction, uncontrolled symptoms, or kidney function concerns, the first step may be urgent drainage rather than immediate stone removal.
- Ureteral stent: a thin tube placed inside the ureter to bypass the blockage and let urine drain.
- Nephrostomy tube: a tube placed through the skin into the kidney to drain urine externally into a bag.
Why this matters: In higher-risk situations, relieving pressure and treating infection comes first. Definitive removal is often scheduled after things stabilize.

Medical expulsive therapy
Some clinicians prescribe medical expulsive therapy (MET) to help the ureter relax and improve the chance of passage for select ureteral stones. The most common medication used is tamsulosin.
The most common side effect people notice is dizziness or lightheadedness, especially when standing up quickly. If you are pregnant, have very low blood pressure, or take other medications that affect blood pressure, your clinician may choose a different plan. If MET is part of your plan, ask how long they want you on it and what symptoms should prompt you to stop and call.
Questions to ask at your next check-in
If you are on the fence about continuing a trial of passage, these questions help you get a clear, medically grounded plan:
- What is the stone size and where is it located in the ureter?
- Do we have evidence of obstruction or hydronephrosis?
- What is our time limit for observation, and what signs mean we stop sooner?
- Do I need repeat imaging, and if so, what type can we use to limit radiation when appropriate?
- Am I a good candidate for medical expulsive therapy (such as tamsulosin), and for how long?
- If we intervene, which procedure do you recommend and why?
- What are the chances I will need a stent, and how long would it stay in?
Bottom line
Waiting can be the right call, but only under the right conditions. A ureteral stone should not be given unlimited time if you are suffering, if it is not progressing, if kidney function is at risk, or if infection is on the table. Fever with stone symptoms is the clearest stop sign, but feeling severely unwell can be a stop sign too, even without a documented fever.
If you are unsure where you fall, you are not being difficult by asking for a reassessment. You are being appropriately cautious with your kidney, and that is exactly the right instinct.
FAQ
How do I know if my stone is “not moving” without imaging?
You often cannot tell for sure based on symptoms alone. Pain can come and go even when the stone is stuck. If progress matters to the decision, repeat imaging is the most reliable way to check location and obstruction.
Is blood in the urine a reason to stop the trial of passage?
Small amounts of blood can happen with stones and can look dramatic. By itself, it is not always an emergency. But blood plus fever, worsening pain, dizziness, inability to urinate, or feeling very ill needs urgent evaluation.
Can I wait longer if the stone is small?
Sometimes, yes. Smaller stones pass more often. But size is not the only factor. Infection, obstruction, kidney function changes, and uncontrolled symptoms override stone size.
If I need a stent, does that mean the stone cannot be removed?
Not necessarily. A stent is often temporary and can be placed after ureteroscopy or as an urgent step to relieve obstruction. Stone removal may happen the same day or later, depending on your situation.